
CMS Is Paying MA Plans More. Will Physicians Be Paid More?
Higher CMS payments to Medicare Advantage plans do not automatically produce higher physician reimbursement. Practices must examine their own MA agreements, fee schedules, financial exposure, and negotiation opportunities to determine what increased plan funding means locally.
CMS has delivered encouraging news for Medicare Advantage beneficiaries heading into 2027. Weighted average premiums are projected to fall, supplemental benefits are expected to remain stable, and most beneficiaries will continue to have broad access to plan choices.
For physicians and medical practices, however, the announcement raises a different question: If Medicare Advantage plans are receiving more from CMS, will providers receive more from the plans?
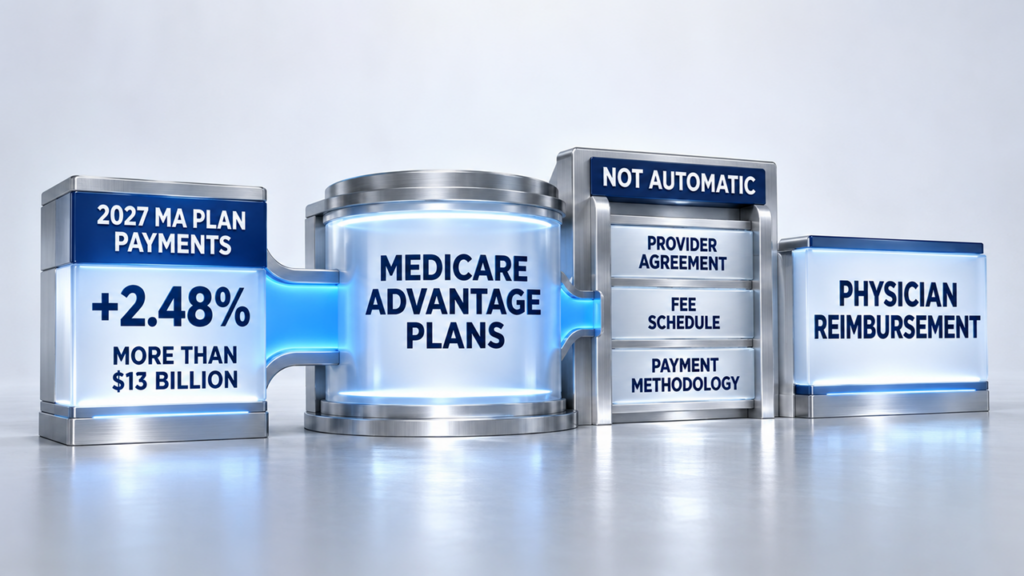
The answer is not automatic. CMS determines what Medicare Advantage plans receive. The agreements practices manage, analyze, and negotiate determine how those plans reimburse physicians.
The 2027 Medicare Advantage Numbers
CMS projects that its finalized 2027 payment policies will produce a 2.48% net average increase in payments to Medicare Advantage plans, representing more than $13 billion. When CMS includes its estimated 2.50% risk-score trend from factors such as population changes and coding practices, the expected average increase reaches 4.98%.
Those figures describe different components of the projection. The 2.48% reflects the expected average effect of the finalized payment policies. The 4.98% includes the separate estimated change in risk scores. Neither figure guarantees that every plan will receive the same increase.
CMS also projects that the weighted average monthly MA premium will decline 16.5%, from $14.37 in 2026 to $12.00 in 2027, while supplemental benefits such as dental, hearing, and vision coverage remain generally stable.
More Plan Funding Does Not Guarantee Higher Physician Rates
The CMS update applies to Medicare Advantage plans. It is not an automatic pass-through to physicians, medical groups, or hospitals. An individual plan’s results will vary according to geography, membership, risk scores, quality performance, utilization, benefit design, and operating costs.
Plans may use additional funding to maintain benefits, lower premiums, absorb medical-cost increases, strengthen reserves, compete for enrollment, or support other priorities. Physician reimbursement changes only when the applicable agreement, fee schedule, or payment methodology changes.
That distinction matters. Original Medicare updates physician payment rules and fee schedules through a public regulatory process. Medicare Advantage reimbursement is governed by the provider’s private agreement with the plan. A practice can therefore experience increasing MA volume without receiving any corresponding improvement in contracted rates.
Medicare Advantage Exposure Deserves Separate Attention
CMS projects that approximately 34 million people will enroll in Medicare Advantage in 2027, representing about 47.4% of all Medicare beneficiaries. CMS also notes that plan projections have historically understated actual enrollment and expects final enrollment to be more robust than current estimates suggest.
For practices, the implication is straightforward: a significant share of Medicare patients may arrive under privately negotiated MA agreements rather than Original Medicare payment rules. Those agreements should be evaluated separately from both commercial payer contracts and Original Medicare reimbursement.
Practice leaders should know:
- Which MA plans represent the greatest patient volume
- How each agreement defines reimbursement
- Which Medicare year, fee schedule, or benchmark controls
- Whether the methodology updates automatically or only at the plan’s discretion
- How modifiers, bundling, and multiple-procedure reductions are applied
- Whether amendment language permits unilateral payment changes
- When renewal, notice, and renegotiation windows open
Without that visibility, an expanding MA population can increase clinical and administrative workload without producing an equivalent improvement in financial performance.
Prepare Before the Next Contracting Conversation
Practices should not begin by asking every plan for the same 2.48% increase. They should begin with their own data.
First, gather every MA agreement, amendment, fee schedule, and reimbursement exhibit. Confirm that the documents are current and identify the methodology governing each major service line.
Next, compare the practice’s frequently performed services with the applicable MA allowable amounts, current Medicare rates, and appropriate market benchmarks. Weight the analysis using actual utilization so the result reflects what the practice performs most often, not simply the codes with the largest percentage differences.
Then evaluate the contract language governing reimbursement updates, amendments, payment policies, notice periods, renewal terms, termination rights, and dispute procedures. The financial opportunity and the contractual path to pursue it must be understood together.
Finally, quantify the request. A stronger contracting position explains how long the rates have been in place, how reimbursement compares with relevant benchmarks, which services are financially misaligned, how patient access or network adequacy may be affected, and what specific change the practice is requesting.
That turns a general appeal for better rates into a documented, practice-specific position.
Turn the CMS Announcement Into a Practice-Level Strategy
The CMS announcement gives practices a timely reason to revisit Medicare Advantage reimbursement, but it does not establish that every plan can or should provide the same increase. The opportunity is to ask informed questions, obtain current reimbursement information, and determine whether each plan’s 2027 payment structure remains sustainable for the practice.
At CodeToolz, we help practices organize MA contracts and fee schedules, identify outdated or unclear reimbursement methodologies, compare rates against relevant benchmarks, quantify financial opportunities, and prepare data-supported negotiation strategies.
The purpose is not to assume that additional CMS funding belongs to the provider. It is to ensure the practice understands its current position and enters the contracting conversation with facts.
Your Next Step
Identify the Medicare Advantage plans responsible for the greatest share of your Medicare patient volume. For each plan, confirm the governing agreement, reimbursement methodology, fee schedule year, renewal date, and negotiation window. Then compare the rates attached to your most frequently performed services with current benchmarks.
If the contract has not been reviewed recently, the rates have remained unchanged, or the reimbursement methodology cannot be clearly explained, the agreement deserves attention.
Building Stronger Payer Strategies
CMS is projecting increased Medicare Advantage plan payments in 2027. Whether physicians are paid more will depend on what their agreements provide and what practices are prepared to pursue.
The plans have their numbers. Your practice should have its numbers too.
Dana R. Bellefountaine Jr. | Founder & CEO | CodeToolz | The Physician’s Advocate in Payer Contracting
#CodeToolz #MedicareAdvantage #PayerContracts #PhysicianReimbursement #ContractNegotiation #HealthcareFinance #MedicalPracticeManagement #ContractAnalysis #FeeSchedules #PhysicianLeadership #HealthcareStrategy



